FOOTLOCKER–43 YEARS LATER

clic the pic

clic the pic

One of the Biggest Little Towns in Laos during the war. The extreme western terminus of the DMZ. The Plain des Jarres Golf and Country Club. Indian Country. 20 Alternate, LS-98, or simply LS-20 A on the map. Whatever you called it, Long Tieng was home to quite of few of us for a while. 

Nestled in the valley below Skyline Ridge and our TRC-28 Microwave shot back to Vientiane, 20 Alternate was a hot town mais non cocottes. If you risked fooling around with one of the beautiful Meo babes, you were headed for a shotgun wedding regardless of whether you had consummated it or not. You had to hitch a ride to Vientiane if you wanted to get laid.

Leaving 20A and going to work

It was the only large airport I’ve ever seen with one way in and the reverse way out- hence the nickname of The one-way runway. You landed on runway 315. You took off on runway 135 which looked and felt remarkably similar. At the end of our runway (landing) were what we called the titty Karsts. Two large unequal, Madonna missile bra-like  projections sprouted up at the end of the runway. They were also referred to as the vertical speed brake and actually stopped a C-123 cold in its tracks in the late sixties.

LS 20 Alternate Approach August '70

Titty Karsts dead ahead

Here’s another, more recent shot looking southeast from the top of the shorter of the two karsts

91785653

clic the pic

This was General Vang Pao’s last stand and it finally fell in 1973 when it was overrun by the Pathet Lao, aided by the Chicoms and NVA Regulars.

ceeI was there for an incredibly short one month and 14 days but what honestly felt like a lifetime. A very brave pilot I became  friends with departed here on 22 February, 1971 and augered in on his way back down to  L-08 (Vientiane). His tour was almost over. I found out about his passing in 2007 while researching my claim and looking for buddy statements. I was about 500 klics southwest at Operating Location C at T-11 in Thailand with Hepatitis went he went in. I came down with it 89 days after almost finding the Golden BB up near the Plain of Jars (September 1970). I was discharged from the civilian hospital on the 24th of February 1971 and never ran into Chuck again. I assumed he’d DEROSed back to the States.

Forty three years. Seems somehow like last week and at the same time, almost a memory of a dream.

resize 2

clic the pic

Posted in All about Veterans, Inspirational Veterans, Vietnam War history | Tagged , , , , , | 2 Comments

VA NEWS RELEASE

unnamedVA has finally released a picture of the new Veterans Benefits Management System (VBMS) computer interface hookup at the Oakland Regional Office. Douglas Bragg, the director of the Oakland Veterans Service Center, pictured here in the ”clean room”, demonstrates how the computer drive is engaged on an actual pdf virtual claims file awaiting adjudication. In the appendix attached,  .pdf as defined by VA was “pretty damn funny” but this appears to be a misprint.

Note the handy tray-server modification for transfer to another location. Under Secretary for Benefits Allison Hickey recently confirmed the launch of the VBMS at all 56 Veterans Service Centers and noted that their IT fellows are just now working out the last of the bugs. VBMS is considered to be the Final Frontier in conquering the pesky claims backlog. There was no mention of which Veterans Service Center was still not connected as there are 57.

In keeping with VA raters’ wishes, the new computer files still resemble the same light-brown color of the original c-files as well as the same size and shape so as to ensure comfort and familiarity with them. Extensive testing proved that personnel were reluctant to let go of the “old look” and needed continuity of product. After a two year test of 18 Regional Offices, the change was instituted system-wide with a  proposed launch date of  January 1, 2015. VA promises to keep us informed of any updates.


Posted in Humor | Tagged , , , , , , , , , | Leave a comment

VA/MEDICARE RULES FOR SOVALDI

downloadHere’s the latest monogram everyone’s been working from to determine who gets the Sovaldi, how much and for how long. Additionally. they are still trying to pawn off the bug juice (Interferon) on those unsuspecting few with Genotype 1A&B who are gently described as “Interferon naive” or virgins. The good news is the the sickest get it first and those with Cryoglobulinemia even get to cut line to the front. Everything in red is as it appears on the circular.

“Sofosbuvir is indicated for the treatment of chronic hepatitis C (CHC) infection as a component of a combination antiviral treatment regimen. Sofosbuvir has established efficacy in subjects with HCV genotype 1, 2, 3 or 4 infection, including those with hepatocellular carcinoma meeting Milan criteria (awaiting liver transplantation) and those with HCV/HIV-1 co-infection.


This document is meant to aid in deciding which patients are appropriate for simeprevir or sofosbuvir therapy during the preparation, discussion and vetting of the comprehensive drug monograph and criteria for use. The most important outcome of the current document is to ensure access to treatment with these agents for patients with advanced disease who are at higher risk for morbidity and mortality from their disease and liver status.”


 Sofosbuvir: Executive summary


Efficacy has been established in HCV GT 1, 2, 3 or 4, including those with HCC meeting Milan criteria (awaiting liver transplantation) and those with HCV/HIV-1 co-infection

Must not be used as monotherapy

Safety and efficacy not established in post-liver transplant patients

Regimen and duration dependent on both viral genotype and patient population

The efficacy of sofosbuvir in a treatment experienced population was done using modeling; a clinical trial was not conducted.

Candidates for all oral therapy with sofosbuvir and ribavirin include genotype 2 and 3 patients, HIV-HCV co-infected patients, persons who are not candidates for interferon-containing therapy and those awaiting a liver transplant

The safety and efficacy of simeprevir and sofosbuvir in combination in the treatment of HCV infection have not been established.


Patient Selection during interim period (prior to Drug Monograph and CFU approval/posting)


Patients with the highest risk of disease advancement should be prioritized to receive sofosbuvir. This group includes all HCV genotypes with compensated or decompensated cirrhosis and pre- liver transplant patients to prevent post-transplant HCV. Additionally, genotype 1 patients who are deemed interferon intolerant can be considered for a treatment regimen of sofosbuvir/ribavirin given for 24 weeks. Patients who have demonstrated documented ongoing nonadherence to prior medications, medical treatment or failure to complete HCV disease evaluation appointments and procedures are not appropriate candidates for therapy until those issues have been resolved.

Cirrhosis/ALD can be defined as

Biopsy proven cirrhosis

or

Clinical diagnosis based on defined events (i.e.,prior Child class B or C qualifying events) , Fib-4 > 3.25, APRI > 2.0

or

Platelet count  < 100,000 mm3

Or

Fibroscan score >12.5 kPa

In addition, consideration should be given to treating patients with serious extra-hepatic complications of HCV infection such as cryoglobulinemia

Interferon ineligible populations include;

·         Patients with severe thrombocytopenia (platelet count < 50,000 mm3)

·         Patients with severe depression not responsive to medical therapy (documented by mental health provider)

·         Patients with decompensated liver cirrhosis, i.e., Child class B or C

·         Patients with hepatocellular cancer awaiting liver transplant

·         Patients with auto-immune diseases that may be exacerbated by interferon-mediated immune modulation

Dosage and Administration for Sofosbuvir

One 400mg tablet QD with or without food

No response guided treatment

Eliminated primarily via renal clearance, safety/efficacy of sofosbuvir is not established in CrCl<30 ml/min

Hemodialysis removes 18% of the dose.

A dose recommendation cannot be made for patients with severe renal impairment (CrCl< 30 ml/min) or end stage renal disease requiring dialysis

No dose adjustment of sofosbuvir is required for patients with mild, moderate or severe hepatic impairment.

Drug Interactions

Sofosbuvir is a substrate of P-glycoprotein: inducers may decrease sofosbuvir plasma concentrations

No CYP450 involvement, fewer drug interactions would be anticipated


 Duration of Treatment with Sofosbuvir, Peginterferon and Ribavirin*

  Regimen Total Treatment  Duration
Genotype 1 or 4 Sofosbuvir + PEG-INF + RBV 1.0-1.2g/day 12 weeks
Genotype 1 or 4 interferon intolerant Sofosbuvir  + RBV 1.0-1.2g/day 24 weeks
Genotype 2 Sofosbuvir + ribavirin 1.0-1.2g/day 12 weeks
Genotype 3 Sofosbuvir + ribavirin 1.0-1.2g/day 24 weeks
Genotype 1-4, pre-transplant Sofosbuvir + ribavirin 1.0-1.2g/day Until time of transplant

*Includes both HCV mono-infected and HCV/HIV co-infected patients


Posted in Sofosbuvir | Tagged , , , , , , , , , , , , , , , , , , , | 3 Comments

USB HICKEY–WE CAN’T SUPPORT THESE “TRIPS”

Waco VSC Drive-Thru Window (circa 2005)

Waco VSC Drive-Thru
Window (circa 2005)

For years and years, the American Legion has had an “action team” that dutifully travels the US and “inspects” the Regional Offices we have now come to know and love as “Veterans Service Centers”. After the millions of dollars spent on the new drive through features for filing in the 90’s,  VA has been proactive and added electronic filing as well. Now VA can lose it and legitimately say they never received it from you. It’s called presti-“digital” manipulation. 

downloadAmLeg considers their Go-Team a much-sought after plumb. You get to travel from city to city. You get to meet with other Vets and show off your hats. AmLeg has a lot of Posts with bars/restaurants and everybody wants to buy drinks for you. It’s a win-win job. There are 57 Veterans Service Centers-not counting the AMC on Eye Street NW. in DC. Imagine taking a trip to Manila, Philippines in December? How about packing the .338 Win-Mag. to Anchorage during the moose rut? If you take three days at each one and allow for vacations and National Holidays, you can start at the first Regional Office you visited exactly one year later and continue this charade parade endlessly. I figure they pack the spinning rod gear, start in Togus in June when the small mouth bass are voracious and work their way over to Fort Harrison, and the Northern Tier trout fishing.  Fall is perfect for Winston Salem and dove/quail hunting. It’s nice to then catch the sunny southern weather in winter and swordfish or blues in the Gulf of Mexico.

Which is why we’re even talking about this. AmLeg showed up as announced at the Seattle Veterans Prize Fulfillment Center recently and got the cold shoulder.  This was not taken well by the AmLeg guys so they retreated to the nearest post, ordered beers and got Alpha 6 Actual on the horn for the “Now what?” briefing. The silvers are running up in the Juan de Fucas and Seattle is being intransigent. A fine how do you do.

Veterans should not find this surprising. As most know, we are renowned for going postal or NASDAQ depending on which part of the country uses which pejorative. That Vets tend to do it inside or in front of VA facilities makes for messy problems and slippery floors. To remedy this, the VAROs have resorted, for the most part, to corraling Veterans into a waiting room with lots and lots of bulletproof glass and easy to clean floors. This is simply for the safety of everyone involved and should not be negatively construed as being adversarial or anti-Vet. In fact, with the way VA hierarchy treats it’s AFGE employees, the B/P glass may be there for them as much as irate Vets.

This “moat around the castle” scenario is just more of the locked cockpit-door idea on  Regional Offices. If Vets can’t get in, they just commit hari-kiri in the waiting area. I’m sure this idea came out of the sixth floor Vermont Ave. hallway suggestion box. The whole idea of the Department of Veterans Affairs is contained in its very name. Perhaps we should gift the VBA a Hooked on Phonics© course and they can learn how to sound out what they’re there for in the first place. We spent three or four years of our lives-some twenty- obeying rules and regulations. When it comes time to cash in the check and collect on the promises, VA tends to pull up the drawbridge and become inaccessible. Kind of like your Service Officer about a day after they get your Power of Attorney.

AmLeg has suddenly encountered the same mentality we get every day and they are shocked. I say shocked. The VA folks are up to their ears in bad publicity, the VBMS is operating more slowly than 1990s dialup or crashing several times a day and the friggin’ AmLeg guys with the funny hats want to come in and wander around unattended. The VA can’t have this. I was there in 2011 on the eleventh floor-the inner sanctum- awaiting my Board hearing. We were assigned a DRO minder who engaged in small talk and tried to ascertain if I was a NASDAQ-kind of guy. The metal detector had already revealed my ballpoint pen daggers and I had been relieved of them before we ascended from the first floor. Imagine having so much adjudication time to burn that they could afford me my very own GS-13 DRO officer? She even brought Cupcake some coffee.

Unfortunately for the AmLeg entourage this year, the VA has tightened up. No more bonuses. No smiles and high-fives in the hallway. Spartan conditions reign. Sequestration probably forced them into using Instant Folger’s in their cup instead of hopping the elevators down to 3 for a Starbucks run. With everyone in such a dour mood, did the AmLeggers honestly believe the VSC Manager was going to greet them with open arms and  “Hail, Fellows.  Well met!” gusto? Wake up and smell that Folger’s , dudes.

VAOIG

click the pic.

We are discovering the obvious truth as VA rearranges the musical chair statistics each month. The backlog is merely growing more tentacles like Medusa. Boldly Going Where No Federal Agency Has Gone Before is beginning look like yet another innovation up on blocks. To add insult to injury, The VA’s very own Office of Inspector General (VAOIG)- the one tasked with unmasking misfeasance- is busy investigating the Veterans Service Center in Cairo adjacent to Denial River. I understand that there are VAMCs and CBOCs throughout the land that are deficient in opioid medication management, but they need to keep hammering on the backlog agenda. From what we’ve read also, I suspect that the OIG should be reviewing VAMC sanitary protocols in their operating rooms .

To be truthful, we need to examine this backlog dilemma like a watchmaker. AmLeg is just one part of the puzzle. If they notice a better way to build a mousetrap while they are there, then the trip was worth it. Remember, they were the first ones to question why there would be a shredder right there in the C-files storage room at the Dayton Veterans Service Center as early as  2006. Once noted, the VAOIG was able to nip the shredding fiasco in the bud by 2009. Nothing gets by the OIG. Eventually they form a posse and head out to investigate.

As for Under Secretary Allison,nobody-least of all her- wants to be holding the bag on January 1, 2015 when they have to start prevaricating and saying “Hold the phone, Congressman Miller. 2015 is 365 days long. We never actually said what actual day in 2015 we’d attain 125-day/ 98% accuracy- so back off. Hear?”

For the record, here’s what Seattle looked like as of February 18th, 2014. Yep. 18,078 Vets. Sounds like much ado over nothing at Fox News.

va

18,076 Vets. 18,077 Vets Vets.18,079 Vets

18,076 Vets. 18,077 Vets.
18,079 Vets


For the record, we haven’t had 25,000 Vets waiting since August 08th, 2012. Well, unless you count the ones waiting for a SOC. And the ones waiting for a Board hearing. Or the ones waiting to have their appeals certified to go to DC. If you count all of them, it’s waaaaay over 35,000 but VA doesn’t count them that way. It’s far too depressing and besides, it’ll all be fixed by 2015 anyway so what’s the big hullabaloo?

Posted in VA BACKLOG, vA news | Tagged , , , , , , , , , , , | 6 Comments

CAVC–FRADKIN v. SHINSEKI–IMPLICIT DENIAL IS STILL A NO-NO

Reversed and remanded!

Reversed and remanded!

Meet Robert Fradkin. An  American eager to serve his country in 1967 and who ended up with bent brain syndrome. VA fought him tooth and nail over this from his discharge in 1971 right up to 2002 when they relented and granted his claim back to his 1995 filing. This case is his fourth trip to the CAVC-some kind of remand record. Apparently, the BVA was not going to admit to what the common meaning of “is” was in 1971. I liken it to a child who is still cussing after he’s had his mouth washed out with soap four times. Our patron Saint of Veterans, Saint Mary Schoelen of the Holy Shrine of 625 Native Americana Ave. NW, has had enough and raises the “you’re outta here” thumb. 

Fradkin reversal pro se

I think what most of you will find amazing is that Mr. Fradkin did this all by himself. Winning a claim is no small feat in this VA Hall of Mirrors. Winning a CUE claim back to 1971 is like batting a .1000.

As usual, this one boils down to semantics. This is VA’s forte when they are controlling the Kangaroo Kourt. It even succeeds at the BVA where they carefully search for any legal justification for a denial. This time, they run afoul of time, too many frivolous technicalities and a pronounced propensity to lump a wealth of  personality disorders and compensable claims in one pile and blend them into puréed confusion. Mr. Fradkin wasn’t buying. He knew he had a brain owie. VA was willing to concede it as well. What they were not going to discuss was whether anything he had might be compensable. Viewed narrowly, his in-service complaint of schizoid personality was noncompensable. But that was not what he complained of. He was talking anxiety disorder and nervous condition.

I liken this technique to how they phrase your claim. You walk in and fill out the 21-526 and say I’m not a doctor but there is something amiss upstairs. VA will run with it and say okay, which one? There’s a pretty long list with a lot that begin with Schizo-. If you pick the wrong one, you lose.  Mr. Clemmons (v. Shinseki) had this very same problem, too. And like Mr. Clemmons, VA felt compelled to pick a mental disease Bob was not suffering from so as to deny it.

The appellant seeks reversal of the Board’s decision, arguing that the Board clearly erred when it determined that his claims for chronic anxiety and depressive neurosis were implicitly denied in the November 22, 1971, rating decision. He argues that he was not put on notice that VA was denying entitlement to service connection for chronic anxiety or depressive neurosis because there is nothing in the rating decision or notice of disallowance that refers or alludes to either diagnosis.

Bingo. Four trips to the CAVC to discover that implicit denial is still illegal in the lower 48? What’s worse, Willy Gunn finally has to fall on his sword and admit it. But four trips to the Big House to get them to admit they were “interpreting it wrong”? Saint Mary decides this is over the top-hence the reversal. You see this a bit more with the newer breed of judges at the Court- especially the more knowledgeable women like Schoelen and Bartley. I  think the jury is still out on Coral W-P but Hagel is even beginning to get fed up with some of this judicial ineptitude. VA should, by rights, only be allowed to commit adultery X number of times before they get charged with patronizing a prostitute.

Here, you get a feel for that laissez faire VA attitude. VA has screwed this up at the RO (1) the BVA (4) and now we are at the Court for the fourth attempt at determining what the truth is. Willy wants to export it back for one more lather, rinse and repeat at the BVA. Shoo-doggies. Like St. Mary is going to fall for that again?

The Secretary concedes that the appellant’s 1971 claims for chronic anxiety and depressive neurosis were not implicitly denied in the November 1971 rating decision and that the Board clearly erred in its application of the factors identified in Cogburn. Accordingly, the Secretary asserts that “remand of [the a]ppellant’s earlier effective date claim is warranted for readjudication and any necessary development.”

Clearly, the marijuana being smoked at the OGC is of a much higher quality than what is being sold in Washington and Colorado. You can almost see the paraphrasing in the brief:   “Well, Miz Schoelen. We gotta apologize. Seems you have it all figured out so just hand it back to us and we’ll sashay on over to Vermont Ave. and “fix” it.”

Schoelen isn’t that naive. She likes to do summaries and list all those mistakes where the Veterans Law Judge “got the vapors”.

 Upon review, the Court will accept the Secretary’s concession of Board error. The Court agrees that nothing in the language of the November 1971 rating decision nor in the December 1971 notice letter provided sufficient information for a reasonable claimant to know that a claim for any nervous condition, including chronic anxiety or depressive neurosis, was denied…

The Court further agrees that the Board erred when it determined that the first and fourth Cogburn factors also weighed in favor of finding an implicit denial…

Finally, with regard to the fourth factor, the Court agrees with the appellant and the Secretary,that the record does not show that he was represented by an attorney when the November 22, 1971,
rating decision issued. See Cogburn, 24 Vet.App. at 217 (finding that whether a claimant is represented by an attorney is relevant to determining “what disability was initially claimed and how
any decision based on the implicit denial doctrine is interpreted“)

Based on the foregoing, the Court holds that the Board clearly erred in determining that the appellant’s claims for chronic anxiety and depressive neurosis were implicitly denied in the
November 22, 1971, rating decision. Gilbert v. Derwinski  (“‘A finding is “clearly erroneous” when although there is evidence to support it, the reviewing court on the entire evidence is left with the definite and firm conviction that a mistake has been committed.'”  As a result, the appellant’s claims remained pending from October 1971 to March 2002 when the Board awarded entitlement to disability compensation for major depression. R. at 1271-80; see Adams v. Shinseki, 568 F.3d at 960 (“If a claim is left pending, it can be addressed when a subsequent claim for the same disability is adjudicated by [VA], in which case the effective date for any award of benefits will be the effective date applicable to the original claim.”)

Accordingly, the Court will reverse the Board’s decision that the appellant is not entitled to an effective date earlier than April 28, 1995, for the award of disability compensation benefits for major depression and remand the matter for (1) assignment of an effective date applicable to the appellant’s original claim filed in October 1971, which was within one year following his discharge from military service, and (2) a determination of the appropriate disability rating or ratings.

If VA continues to shoot themselves in the same foot again and again, I suppose they shouldn’t be surprised to get this treatment.

Here’s another by Judge Hagel. Same problem. This time the semantic slip up was blamed on the Vet-one Victor Ortiz-Alvarado- for using the word “revise” instead of “reconsider”. Pretty cheeky, huh?

Ortiz-Alvarado reversal on MFR or CUE

Once the misunderstanding was firmly ensconced, VA proceeded to do what Alvarado most definitely did not ask for- a motion to revise. Remember when your older sisters used to play dumb and try to misconstrue what it was you wanted-like maybe to get into the bathroom before you peed your pants? VA is no different. They’ve just taken it a step beyond to an art form. Unfortunately, CAVC judges usually can see through the ruse unless they are pro-VA jerks like Davis and Kasold are rumored to be.

FradkinAs I point out on these Cliff Notes® forays into reversals, VA usually has done something egregious and repeatedly, or the error is so prejudicial and a deprivation of all that is judicially holy as to warrant the ultimate sanction. Reversals are a repudiation of any redeeming judicial mores in a decision. It is the complete refusal to read into the VLJ’s aspirations any glimmer of nonadversarial justice. In Fradkin’s case the Court gave them three opportunities to do the right thing. When they couldn’t (or wouldn’t), the wrath of Khan was foreseeable.

Posted in CAVC Knowledge, CAVC ruling, CAVC/COVA Decision, Implicit denial | Tagged , , , , , , , , , , , | 4 Comments

PERSON OF INTEREST// NOFORN

securedownloadThis just in from, well, I can’t say who. We’re on top of it but I want everyone to be aware. Please delete after receipt and scrub your browsers. If this website is suddenly shut down and I can no longer be contacted, you’ll know why. I personally believe this may have major consequences in 2016 if it is picked up by the mainstream press. That is, assuming they choose to run it. 


Posted in Humor | Tagged , , , , , , , | 5 Comments

SEMPER FI CLUB

marine

crusty old Marine

Imagine if you can, a groundpounder with airborne wings coming up with a good Marine joke without an Air Force member present to translate it into recognizable, written English. Nevertheless, that is what happened. I’m calling Ripley’s. They’ll never believe it. From the law offices of LawBob.

A minister was seated on a plane bound from Hong Kong to the US with a stopover in Honolulu .

After the stopover a crusty old Marine boarded and as fate would have it, he was seated next to the minister.

 After the plane was airborne, drink orders were taken.

 The flight attendant asked the Marine if he wanted a drink. The Marine told her a Rum & Coke would be fine, which was prepared and placed before him.

 The flight attendant then asked the minister if he would like a drink.

 He replied in disgust….. “I’d rather be savagely raped by a dozen whores than let liquor touch my lips.”

 The old Marine quickly handed his drink back to the attendant and said, ” Whoa there darlin’. You didn’t tell me we had a choice.”

7eQIJIo

National Museum of the Marine Corps Today

Posted in Humor | Tagged , , , , , , , , , , , , , , | 1 Comment

FACEPLACE RAINBOWS

1656431_436214863175994_444433771_nThe pot of gold is in my garden if you believe what you see. I see it as a good sign for a good year of corn. 

Of course, Cupcake had to walk outside and spoil it by taking a picture out back. No rainbow anywhere close to the food production facility.

894058_10202398627064685_1790495489_o

1404403_10202398627144687_774597386_o

And then it started hailing.

Posted in FACE HUMOR | Tagged , , , , , , , | Leave a comment

VA Public Health’s weak online response to the HCV veteran study

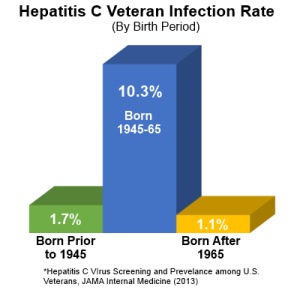
Does anyone sense any urgency in about the VA’s response to the information given in study I posted about previously?  They post one graphic showing an overall 20 year infection rate of 10.3 which is shocking enough.  They offer one horrendous statistic:

davey-110px

Our mission and programs are carried out under the leadership of
Victoria J. Davey, Ph.D., M.P.H., R.N., Chief Officer.

The Veterans Health Administration’s Office of Public Health-Population Health group, reports that baby boomer Veterans had a Hepatitis C infection rate more than five times higher than other Veterans.

Veterans born in 1954 had the highest infection rate at 18.4 percent.

But then they divert attention to the CDC’s recommendation for one-time testing of all boomers. Then they link to the study that involves a lengthy registration and only the study abstract!

September 9, 2013, Hepatitis C Virus Screening and Prevalence Among US Veterans in Department of Veterans Affairs Care

JAMAIntMed Backus HCV Screening Prevalence 2013 173 1549-52

hcvgraphic300-0913

Twenty-year graphic

Victoria Davies, leader of VA’s Dept. of Public Health, why haven’t you set up a call bank to notify every veteran born in 1954 first, every black veteran in the boomer cohort, and then everyone else at risk? Why is there no outreach to veterans in private care and private physicians? This is an extraordinary situation and the VA’s response is lazy, unprofessional, and unethical.  This is worse than Egypt’s HCV crisis that was caused by dirty injections years ago.

Bernie Sanders, please call an investigative hearing on this deplorable lack of action soon!  Victoria Davies has some explaining to do to the Black, Hispanic and overall boomer veteran communities. 

Posted in Guest authors, HCV Health, HCV Risks (documented), Jetgun Claims evidence, Medical News, Nexus Information, VA Medical Mysteries Explained | Tagged , , , , , , , , , , , , , , , , , , , , | 3 Comments

Related Medical Ailments due to Hep-C

head-to-toeHarming more than just the liver, seven other areas of the body are frequently affected by Hepatitis C infection.


Hepatitis C is a common, infectious virus that targets the liver; yet this illness can affect many other parts of the body. Because we generally don’t equate a long list of health issues with the liver, many don’t recognize the connection between Hepatitis C and a vast array of ailments.

Studies have found that between 70 and 74 percent of those with Hepatitis C experience extrahepatic manifestions – conditions that affect organs other than the liver. In hopes of prompting those infected to stay as healthy as possible, below is a list of seven other areas that can be impacted when the liver is continuously battling against the Hepatitis C virus.

  1. Brain – When Hepatitis C infection causes enough liver damage to impair this organ’s ability to filter the blood, toxins can build up in the bloodstream. Unfortunately, accumulated toxicity may damage the central nervous system and impair brain function. Known as hepatic encephalopathy, symptoms may include confusion, forgetfulness, poor concentration, personality changes, abnormal shaking, agitation, disorientation, slurred speech and, in the most severe cases, coma. By aiding detoxification, supplementing with a comprehensive nutraceutical can help prevent brain involvement via inhibition of toxin accumulation.
  2. Eyes – An inflammatory disease that damages the salivary glands causing dry mouth and eyes, sialadenitis has been associated with Hepatitis C infection. In addition, Sjogren’s Syndrome (SS) is an autoimmune disease that renders the eyes and mouth dry. SS is found more often in people with Hepatitis C than in the general population. Although the exact physiology is not well understood, Hepatitis C seems to increase susceptibility to eye troubles. To protect eye health, consider providing your eyes with the nutrition needed to function optimally.
  3. Thyroid – Part of the endocrine system, the thyroid gland delivers hormones into the bloodstream. In certain individuals, the Hepatitis C virus may cause the immune system to mistakenly injure the thyroid – either causing overactivity (hyperthyroidism) or underactivity (hypothyroidism). Hypothyroidism may lead to feeling sluggish and cold while hyperthyroidism can cause symptoms such as nervousness and rapid heartbeat. Supplying the body with the thyroid-nourishing vitamins, minerals and botanical extracts  can help protect this valuable gland.
  4. Joints and Muscles – According to the American College of Rheumatology, it is common for people with Hepatitis C to have related rheumatic diseases – problems affecting the muscles, joints and connective tissue. The joint and muscle complications of Hepatitis C result when the body’s immune system fights against the virus. One of the most common causes of joint and muscle pain with Hepatitis C is rheumatoid arthritis, a painful condition characterized by inflammation of the synovial joints.
  5. Digestion – Many who undergo Hepatitis C treatment suffer with digestive problems like low appetite, nausea and abdominal distention. Even those not taking antivirus therapy are vulnerable to digestive issues. Because the liver plays an important role in the digestive system, many with Hepatitis C experience upset stomach, diarrhea and abdominal cramps. Although a physician should always be consulted about these symptoms, many of these digestive problems are aided by re-colonizing the gastrointestinal tract with a powerful probiotic supplement.
  6. High Blood Sugar – A healthy liver helps convert sugars into glucose and store it for energy. Too much sugar in the bloodstream can lead to insulin resistance or type 2 diabetes. Part of a collection of health problems termed metabolic syndrome, high blood sugar is frequently accompanied by obesity, high blood pressure and a fatty liver. An increasing number of studies are showing that high blood sugar, insulin resistance and diabetes are seen more often in those with Hepatitis C than the general population. While eating low glycemic index foods and exercising regularly are the best ways to avert high blood sugar.
  7. Hands and Feet – A painful condition that affects the blood vessels in the fingers, toes, ears and nose, Raynaud’s phenomena is a disorder that causes the blood vessels in extremities to constrict. A potential Hepatitis C extrahepatic manifestation, cryoglobulinemia is a blood disorder caused by abnormal proteins that clump together when blood is chilled. In people with Hepatitis C-related cryoglobulinemia, one study found that 30 percent of affected individuals also had Raynaud’s phenomenon. Preventing this problem is best achieved by quitting smoking, exercising regularly and keeping out of extremely cold temperatures.

From your head down to your toes, Hepatitis C infection can wreck havoc just about everywhere. These seven areas of the body do not represent every possible target for Hepatitis C; however, they certainly cover a large portion of this virus’s extrahepatic manifestations. Shielding the liver from this virus will help minimize liver damage, but it should not be the only therapeutic approach. Depending on where your vulnerability lies, it makes sense to expand Hepatitis C wellness routines accordingly. Whether you notice confusion and forgetfulness, signs of metabolic syndrome, sluggishness, diarrhea and nausea, cold extremities or inflamed joints, providing applicable nutritional support and/or lifestyle adjustments can ease the burden of many extrahepatic manifestations.

Posted in Guest authors, HCV Health, HCV Risks (documented), Jetgun Claims evidence, Medical News, Nexus Information | Tagged , , , , , , , , , , , , , , , , , , | 5 Comments